
Breastfeeding is natural, but it is not always easy. Most new mothers expect it to come easily and are discouraged when it does not. Sore nipples, an unsettled baby, uncertainty about whether enough milk is coming through; these are among the most common experiences in the first weeks, and they send many mothers spiralling into doubt about whether they can do this at all.
The good news is that the vast majority of breastfeeding difficulties are solvable. Understanding how breastfeeding works, what the early challenges typically are, and how to address them makes a real difference. This newborn breastfeeding guide covers what new mothers actually need to know, from getting the latch right to building and protecting milk supply.
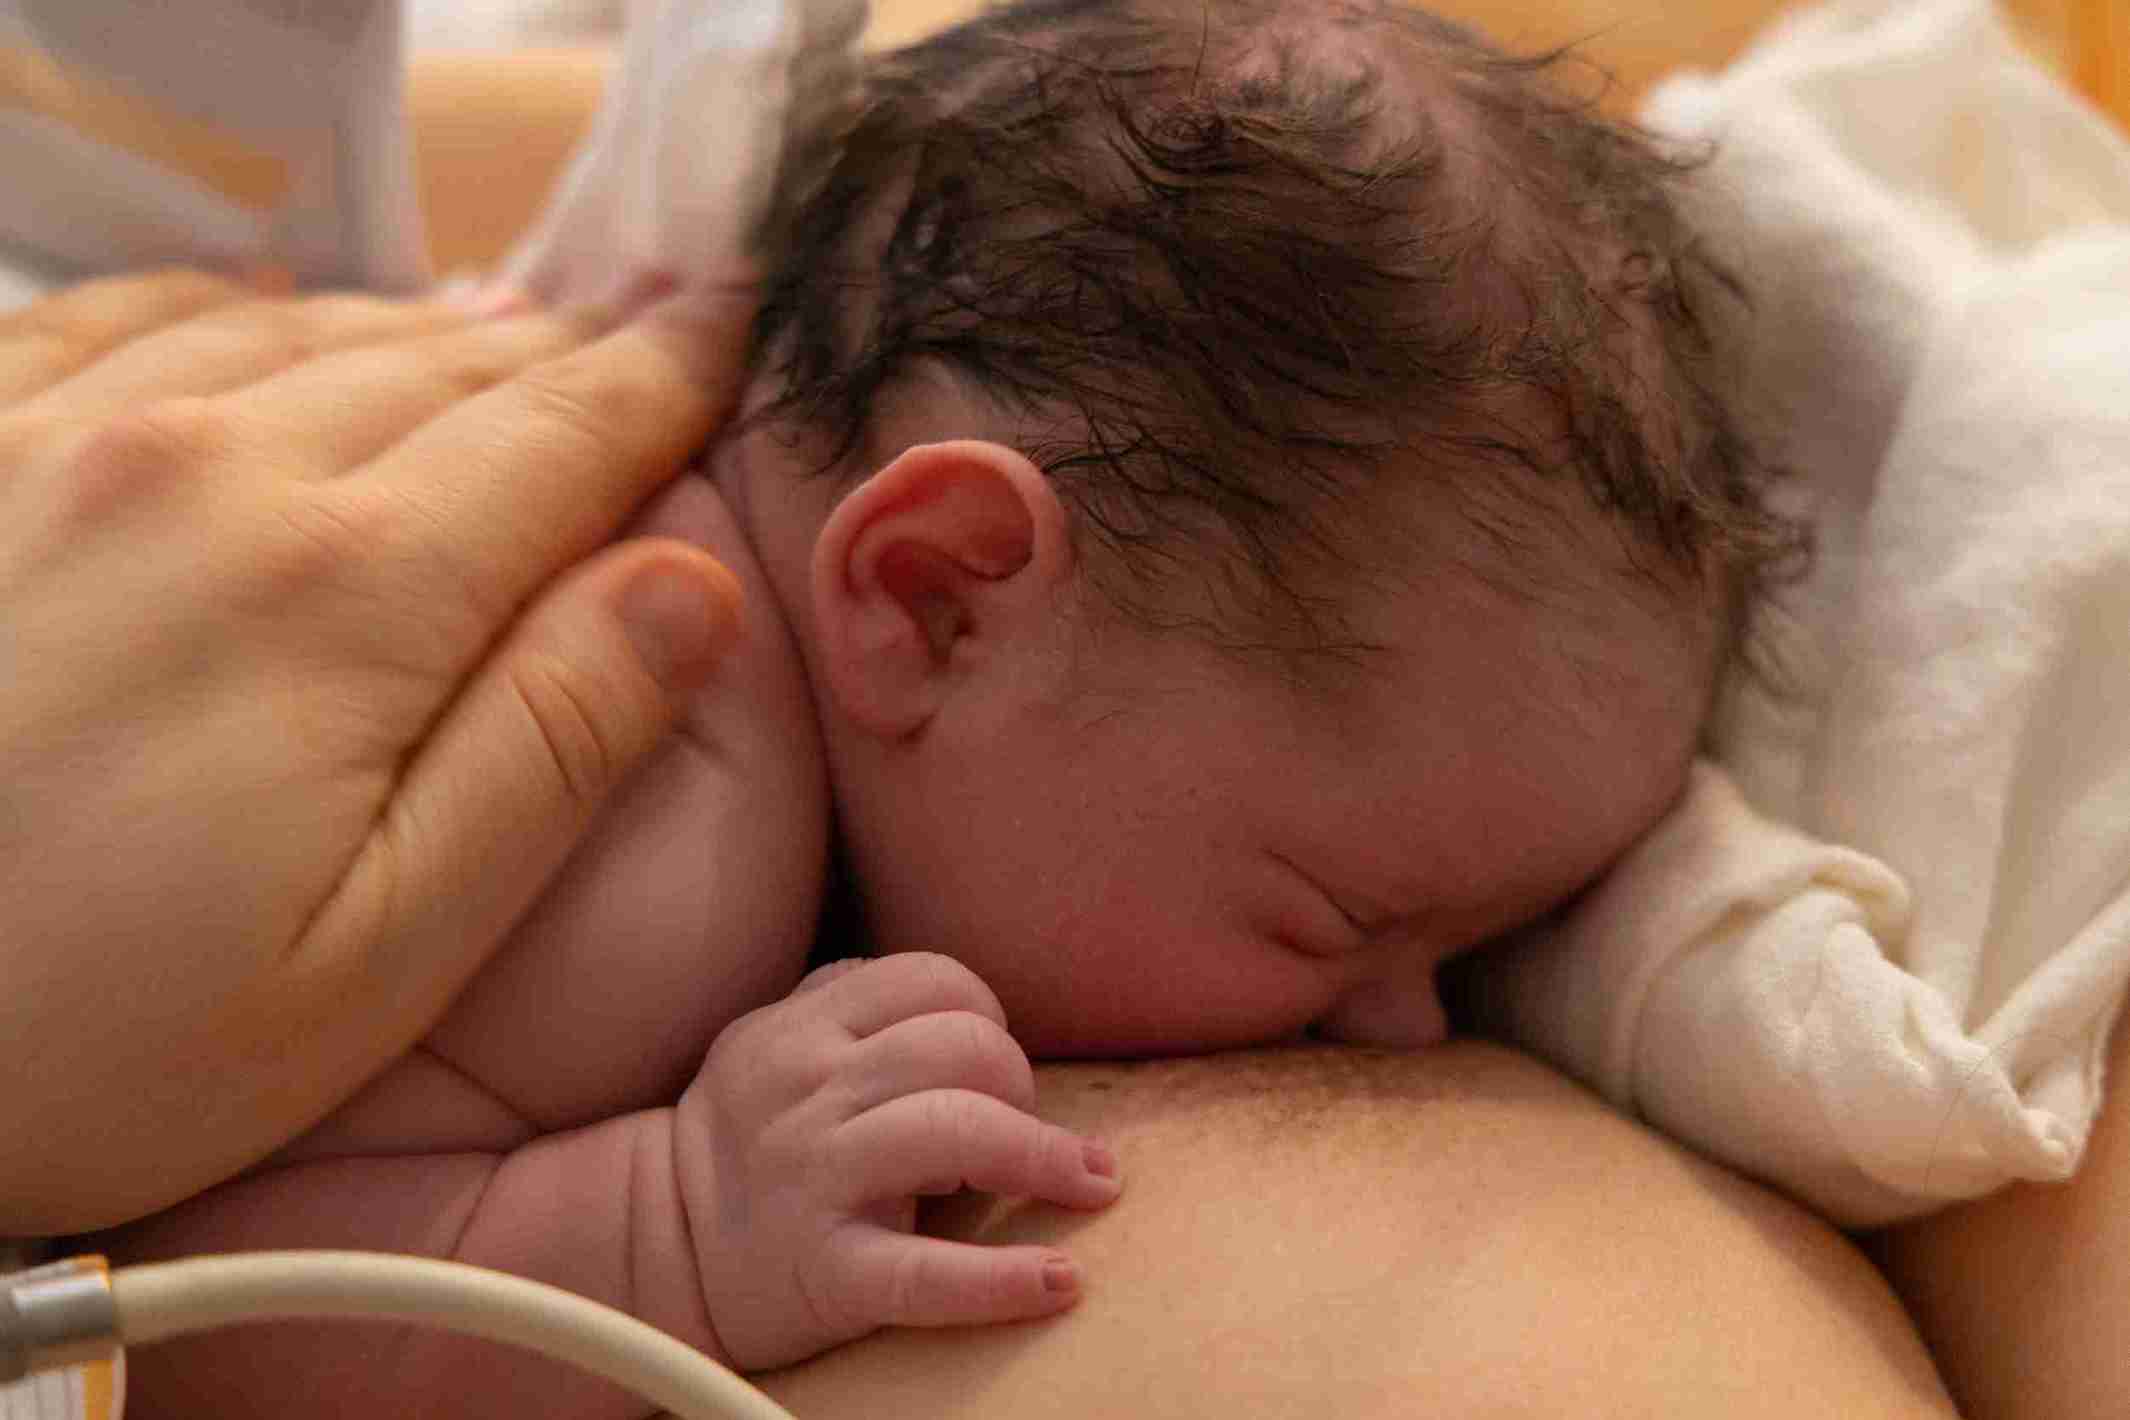
Breast milk production works on supply and demand. The more the baby feeds and the more effectively they transfer milk, the more milk the body produces. This is the fundamental principle on which everything else builds.
In the first few days, the breasts produce colostrum, a small amount of thick, yellowish fluid rich in antibodies, immune factors, and concentrated nutrients. Colostrum is produced in very small volumes for a reason. A newborn's stomach at birth is the size of a marble. By day 3, it is the size of a walnut. By week two, it is closer to an egg. The volume of milk increases to match.
Full milk comes in between days 3 and 5 for most women. When it does, the breasts may feel very full, heavy, and tight; this is called engorgement. Frequent feeding is the main way to manage it. The fullness eases as supply calibrates to the baby's actual demand, usually within 1-2 weeks.
Correct latching is one of the most important breastfeeding techniques to master. Most early breastfeeding problems, like sore nipples, poor milk transfer, and an unsettled baby, trace back to an incorrect or shallow latch.
If the latch is wrong, do not continue through the pain. Break the suction by gently inserting a clean finger into the corner of the baby's mouth, and start again.

There is no single correct position; the best one is whatever allows both mother and baby to be comfortable and the latch to be good.
Cradle hold is the most common position. The baby lies across the front of the body with the head in the crook of the elbow. Works well once breastfeeding is established.
Cross-cradle hold is when the baby lies across the body, but the opposite arm supports the baby. The feeding-side hand supports the breast. This allows for more control and is useful for newborns and for improving latch.
Football hold is when the baby is tucked under the arm like a clutch bag, with the legs pointing behind the mother. This position is useful after a C-section and for mothers with large breasts.
Side-lying, where both mother and baby lie on their sides facing each other. This position is useful for night feeds and for mothers recovering from a caesarean.
Most women who worry about low milk supply actually have an adequate supply; the more common problem is how effectively the baby is suckling, not the amount being produced. However, for women with genuinely low milk supply, the following approaches work.
Feed more frequently: The most effective way of increasing breast milk naturally is to increase the number of times the baby is at the breast. Milk production is driven by the amount removed. Feeding 8-12 times in 24 hours is the target in the early weeks.
Ensure effective milk removal: Frequent feeding only builds supply if the milk is being transferred effectively. A poor latch means the baby is drinking less breast milk per feed, which signals the body to produce less. Getting the latch right is, therefore, foundational.
Offer both breasts at each feed: Start on one side, allow the baby to finish that side, then offer the second. This stimulates both breasts and helps build supply on each side.
Rest and hydration: Extreme exhaustion and dehydration affect milk production. Drink water consistently throughout the day; aim for 8-10 glasses. Sleep when the baby sleeps, even if it's only for a brief period.
Skin-to-skin contact: Holding the baby against the bare chest stimulates oxytocin and prolactin, the hormones that drive milk letdown and production.
Foods traditionally believed to support milk supply — methi (fenugreek) seeds, garlic, ajwain, and dry fruits are commonly given to new mothers in Indian families.

A lactation consultant is a trained specialist in breastfeeding support. Getting help from one early is far more effective than struggling alone for weeks. Seek lactation consultation if:
The WHO, Indian Academy of Paediatrics, and most major health bodies recommend exclusive breastfeeding for the first 6 months. After six months, solid foods are introduced alongside continued breastfeeding, which is recommended for at least two years or as long as the mother and baby wish. In the first six months, the baby does not need water; breast milk provides all the fluid the baby needs.
Breastfeeding takes practice; for both the mother and the baby. The first 2-4 weeks are the hardest, and they pass. Get the latch right, feed frequently, rest when you can, and ask for help without hesitation when something is not working. A lactation consultant can turn a difficult breastfeeding experience around in a single session. The effort in the early weeks is worth it for both mother and baby.


Seek lactation consultation if the baby is not latching despite several attempts, feeding is consistently painful, nipples are cracked or bleeding, the baby is not gaining weight after two weeks, or you suspect a tongue-tie. Do not wait until you are exhausted and ready to stop breastfeeding — getting help early in the first week or two is far more effective than troubleshooting after weeks of difficulty have built up.
A poor latch is the most common breastfeeding technique problem and is almost always correctable. Break the suction and try again — wait for the baby to open wide, then bring them onto the breast with the mouth covering a large portion of the areola. If repeated attempts do not help, see a lactation consultant. Tongue-tie — a tight membrane under the tongue — is a common physical reason for poor latching and can be treated with a simple procedure.
Increasing breast milk naturally starts with feeding more frequently — 8 to 12 times in 24 hours. Ensure the baby is latching well so milk is being transferred effectively. Offer both breasts at each feed. Avoid unnecessary formula top-ups. Stay well hydrated and rest between feeds. Skin-to-skin contact supports hormone production. If supply remains low despite these steps, a lactation consultant can assess whether an underlying issue is affecting production.
Exclusive breastfeeding — breast milk only, no water or other food — is recommended for the first six months. After six months, solid foods are introduced alongside breastfeeding, which is recommended to continue for at least two years. In the first six months, the baby does not need water even in Indian summers — breast milk provides complete nutrition and hydration. Starting solids before six months is not recommended unless advised by a paediatrician.


 Best Gynecologists in Bellandur Best Gynecologists in Electronic City Best Gynecologists in HRBR LayoutBest Gynecologists in Jayanagar Best Gynecologists in Kanakapura RoadBest Gynecologists in Malleswaram Best Gynecologists in Nagarbhavi Best Gynecologists in Old Airport RoadBest Gynecologists in Sahakarnagar Best Gynecologists in Sarjapur RoadBest Gynecologists in ThanisandraBest Gynecologists in Varthur RoadBest Gynecologists in Whitefield Best Gynecologists in Industrial Area Phase IIBest Gynecologists in OMRBest Gynecologists in T NagarBest Gynecologists in New Industrial TownBest Gynecologists in IndirapuramBest Gynecologists in Golf Course RoadBest Gynecologists in Sector 14Best Gynecologists in Sector 47Best Gynecologists in Banjara HillsBest Gynecologists in GachibowliBest Gynecologists in Hitech CityBest Gynecologists in KompallyBest Gynecologists in Gomti NagarBest Gynecologists in MaladBest Gynecologists in NerulBest Gynecologists in VashiBest Gynecologists in Kailash ColonyBest Gynecologists in PatparganjBest Gynecologists in Punjabi BaghBest Gynecologists in VikaspuriBest Gynecologists in Gaur CityBest Gynecologists in Pari ChowkBest Gynecologists in Sector 51Best Gynecologists in Sector 5 Swastik ViharBest Gynecologists in Kalyani NagarBest Gynecologists in SB RoadBest Gynecologists in Pimple SaudagarBest Pediatricians in BellandurBest Pediatricians in Electronic CityBest Pediatricians in HRBR LayoutBest Pediatricians in JayanagarBest Pediatricians in Kanakapura RoadBest Pediatricians in MalleswaramBest Pediatricians in NagarbhaviBest Pediatricians in Old Airport RoadBest Pediatricians in SahakarnagarBest Pediatricians in Sarjapur RoadBest Pediatricians in ThanisandraBest Pediatricians in Varthur RoadBest Pediatricians in WhitefieldBest Pediatricians in Industrial Area Phase IIBest Pediatricians in OMRBest Pediatricians in T NagarBest Pediatricians in New Industrial TownshipBest Pediatricians in IndirapuramBest Pediatricians in Golf Course RoadBest Pediatricians in Sector 14Best Pediatricians in Sector 47Best Pediatricians in Hitech CityBest Pediatricians in Banjara HillsBest Pediatricians in GachibowliBest Pediatricians in KompallyBest Pediatricians in Gomti NagarBest Pediatricians in MaladBest Pediatricians in NerulBest Pediatricians in VashiBest Pediatricians in Kailash ColonyBest Pediatricians in PatparganjBest Pediatricians in Punjabi BaghBest Pediatricians in VikaspuriBest Pediatricians in Gaur CityBest Pediatricians in Pari ChowkBest Pediatricians in Sector 51Best Pediatricians in Sector 5 Swastik ViharBest Pediatricians in Kalyani NagarBest Pediatricians in SB RoadBest Pediatricians in Pimple Saudagar


